
October 22, 2026
Comparing Digital Lenses: Midtown, Costco & Warby Parker
A fair comparison of digital lens designs, fitting measurements, coatings, materials, and follow-up when choosing glasses in Santa Cruz.
Read more
Myopia Control
Stellest, MiSight, and 0.05% atropine in Santa Cruz, with IOLMaster eye-length monitoring, an interactive study explorer, and primary research links.

Editorial update: October 23, 2026 · Midtown Optometry
Myopia management helps slow a child’s worsening nearsightedness. At Midtown Optometry in Santa Cruz, we primarily recommend Stellest spectacle lenses, followed by MiSight 1 day contact lenses and, when appropriate, 0.05% atropine. The right choice depends on your child’s prescription, age, eye growth, and daily routine.
Explore treatment outcomes · Axial length by age
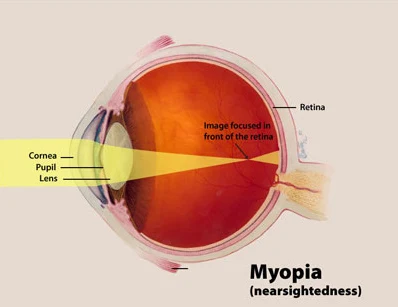
Myopia often develops as the eye grows too long. Ordinary glasses bring distant objects into focus. Purpose-designed myopia-control lenses also deliver an optical treatment intended to slow progression. Higher myopia is associated with a greater lifetime risk of retinal detachment, myopic macular disease, and glaucoma. Treatment aims to slow further progression. An appropriate prescription and ongoing eye-health monitoring remain important.
We measure both the prescription and axial length—the length of the eye from front to back—with our ZEISS IOLMaster optical biometer. Following both measurements gives us a better picture than a glasses prescription alone.
Optical biometry measures axial length using light. It gives us a numerical record of the eye’s front-to-back length. Prescription and axial length provide complementary information: focusing power also depends on the cornea and the eye’s internal lens. We compare serial measurements with age, examination findings, prescription change, and treatment adherence.
A study of 95 myopic children found repeatable axial-length measurements with an IOLMaster. Reliable follow-up still depends on fixation, scan quality, and consistent measurement methods; a tiny change at a single visit can reflect measurement variability. We assess the trend and each child’s clinical context. Read the original IOLMaster study · Research on age and measurement variability.
Alongside growth measurements, our recommended retinal photographs, screening five-line raster OCT, and anterior-segment images help document eye health over time. These images and axial length answer different questions. How our diagnostic tools complement each other.
Axial length changes with age and varies with sex, body size, ancestry, and refractive error. These published population averages include children across refractive categories. Your child’s own growth trend, prescription, and corneal curvature give a measurement its clinical context.
| Age | Mean length | Standard deviation | Population |
|---|---|---|---|
| 6 years | 22.36 mm | 0.75 mm | Generation R, Netherlands |
| 9 years | 23.10 mm | 0.84 mm | Generation R, Netherlands |
| 15 years | 23.41 mm | 0.86 mm | ALSPAC, UK |
Standard deviation describes the spread of measured values. These reference points help interpret the population distribution. A treatment target or diagnosis requires an individual assessment. Source: Tideman et al., Acta Ophthalmologica, 2018.
A separate study of 2,997 Taiwanese schoolchildren produced age- and sex-specific centile curves. Its medians differ from European cohort averages; many older children in this population already had myopia.
| Age | Male | Female |
|---|---|---|
| 6 years | 22.57 mm | 22.32 mm |
| 12 years | 24.34 mm | 23.72 mm |
| 18 years | 25.25 mm | 24.70 mm |
These medians describe the sampled population; they do not define healthy eye length or a universal Santa Cruz reference. Liu et al., 2025: full centile table and study methods.
At Midtown, our ZEISS IOLMaster measures axial length so we can compare repeat measurements over time alongside the prescription. Your clinician interprets the pattern and discusses whether the treatment plan needs adjusting.
Stellest lenses combine a clear central prescription zone with surrounding highly aspherical lenslets. These lenslets create a pattern of light defocus designed to reduce the stimulus for excessive eye growth. Your child wears them as glasses, making them a practical first conversation for families who prefer a non-contact-lens option.
The FDA authorized Stellest in September 2025 for children 6–12 years old when treatment begins, within the device’s prescription criteria. The two-year data reviewed by the FDA showed 71% less progression in prescription and 53% less axial elongation compared with single-vision control lenses. These percentages express relative differences in progression between study groups. Individual children’s outcomes varied. Some participants reported blur or halos. Read the FDA summary.
Consistent wear and a well-fitted frame matter. We check the prescription, fit, adaptation, and measurements over time. A separate randomized trial of highly aspherical lenslets supports this approach; its participants and study design differ from the FDA-reviewed study. Read the randomized spectacle-lens trial.
MiSight lenses use alternating vision-correction and treatment zones. The correction zones help your child see clearly; the treatment zones create myopic defocus intended to slow eye growth. Each lens is used for one day and discarded. We teach insertion, removal, and hygiene, and check that your child and family feel ready for contact-lens care.
In a three-year randomized trial enrolling 144 children aged 8–12, the MiSight group had 59% less prescription progression and 52% less axial elongation than the single-vision contact-lens group. The average changes were −0.51 versus −1.24 diopters and 0.30 versus 0.62 mm, respectively; 109 children completed the trial. Read the original MiSight trial.
In the United States, MiSight is FDA-approved for eligible children aged 8–12 at the start of treatment. Your doctor checks the full prescription criteria. Daily disposal does not eliminate infection risk: no sleeping, swimming, showering, or tap-water exposure with lenses. Pain, redness, light sensitivity, or reduced vision warrants prompt assessment.

Midtown uses 0.05% atropine for myopia management. Atropine drops affect signaling involved in eye growth; the exact mechanism of myopia control is still being studied. Glasses or contact lenses provide the vision correction a child still needs. We consider them when a child’s needs, progression, or tolerance make medication appropriate, and sometimes discuss combination care. Your doctor prescribes treatment and an individual follow-up schedule.
The one-year LAMP trial enrolled 438 children aged 4–12. With 0.05% atropine, average prescription change was −0.27 diopters versus −0.81 with placebo; axial growth was 0.20 versus 0.41 mm. The effect depended on concentration. Read LAMP’s original randomized trial.
Concentration and study population both matter: a U.S. randomized trial found no benefit from 0.01% atropine over placebo after two years. Atropine for myopia management is an off-label use in the United States. Possible effects include light sensitivity, larger pupils, near blur, and irritation. We discuss benefits, uncertainties, and the possibility of faster progression after stopping. Read the U.S. trial and five-year LAMP follow-up.
Published follow-up now extends to five years for Stellest / HAL, six years for MiSight, and five years of continued 0.05% atropine. Later comparisons require attention to study design. HAL’s five-year paper uses an extrapolated standard-correction group after year two. MiSight’s original controls started treatment after year three. LAMP’s placebo group switched to atropine after year one.
Five-year HAL paper and data table · Six-year MiSight paper · Five-year LAMP paper.
The explorer extends the untreated comparison to five years for atropine and six years for MiSight using a labeled mathematical model. Dashed lines continue each trial’s untreated averages with progressively smaller annual changes as children age. The MiSight extension assumes 10% annual slowing of prescription progression; the atropine extension uses 9.7%. Both assume 15% slowing of axial growth. These are calculations made for this site using published methods. They illustrate group-average possibilities and carry uncertainty beyond the measured comparison periods. MiSight’s published modeling method · Five-year extrapolation methods · Axial-growth meta-regression.
The explorer identifies these differences beside the results. Its separate stopping-treatment summaries include MiSight’s seventh year and LAMP’s eight-year follow-up, published in 2026. The eight-year report studies discontinuation strategies during years six through eight. Treatment duration and stopping decisions remain part of your child’s care plan.
Choose a starting prescription and explore published treatment averages: up to five years for Stellest / HAL and 0.05% atropine, and six years for MiSight. Comparison groups and evidence limits are identified with each result.
These are illustrative study averages. Your child’s response can differ. Each treatment uses its own trial, population, and follow-up period; the controls change when you switch studies.
Illustrative outcome after 2 years · age 12
Eye growth: +0.69 mm
Eye growth: +0.34 mm
Difference between the displayed rounded means: 0.80 D less myopic change and 0.35 mm less eye growth over 2 years.
Hundredths of a diopter reflect study averages. Your child’s actual glasses prescription comes from their examination.
Treatment study: Stellest / HAL, 2-year results
More myopic prescriptions appear higher on the chart. Solid treatment lines connect observed follow-ups for orientation; dashed comparison lines show modeled years. Individual paths vary, and cohort membership can change between reports.
| Follow-up / source | Treatment change | Comparison change |
|---|---|---|
| Year 1 | −0.27 D+0.13 mm eye growthObserved treatment study | −0.81 DSingle-vision glasses · +0.36 mmObserved comparison study |
| Year 2 | −0.66 D+0.34 mm eye growthObserved treatment study | −1.46 DSingle-vision glasses · +0.69 mmObserved comparison study |
Adult population studies associate stronger myopia with more eye disease. The table applies those published prescription categories to the available scenarios. Numbers are odds ratios versus nonmyopic eyes, with 95% confidence intervals. An odds ratio of 3 means three times the odds; it gives no personal percentage or timeframe.
These associations provide context if a similar prescription persists into adulthood. Childhood treatment trials have yet to establish a personal lifetime disease probability or a treatment-specific reduction in these outcomes.
| Eye condition | Single-vision glasses | Treatment category |
|---|---|---|
| Myopic macular degeneration | 72.74× odds95% CI 33.18–159.48 | 13.57× odds95% CI 6.18–29.79 |
| Retinal detachment | 8.74× odds95% CI 7.28–10.50 | 3.15× odds95% CI 1.92–5.17 |
| Posterior subcapsular cataract | 2.55× odds95% CI 1.98–3.28 | 1.56× odds95% CI 1.32–1.84 |
| Open-angle glaucoma | 2.92× odds95% CI 1.89–4.52 | 1.59× odds95% CI 1.33–1.91 |
The glaucoma estimate combines moderate and high myopia. Broad categories create steps at −3.00 and −6.00 D; real biology changes continuously. Matching categories can display the same association even when prescriptions differ. Large macular-disease odds ratios reflect a rare outcome in the reference group and wide uncertainty.
Haarman et al., 2020: original meta-analysis · Underlying primary studies: retinal-detachment case-control study and Blue Mountains glaucoma study.
Chinese children aged 8–13; starting spherical equivalent −0.75 to −4.75 D. The randomized trial enrolled 170 children across three groups.
HAL means highly aspherical lenslets, the optical design used in Stellest. One- and two-year selections use the original treatment-group results; longer selections use the five-year completer cohort. Clinical prescribing eligibility is assessed separately.
The prescription scenario is starting spherical equivalent + the stated observed or modeled mean refractive change. Optional axial-length scenarios use measured starting length + the stated mean elongation where verified. Averages are applied unchanged within each study’s supported entry range; this calculation has no validated personalization for age, ancestry, past progression, or adherence.
Individual responses vary around the average, and these trials involved different children and control groups. The display supports discussion of each trial. A direct treatment ranking would require a suitable head-to-head comparison. Longer HAL comparisons use the paper’s modeled standard-correction group. For MiSight and atropine, the dashed extensions are calculated here from each trial’s untreated means and published age-slowing assumptions. Those later control values are model-based estimates. Standard deviations describe variation among participants; standard errors describe precision of a group mean. Neither supplies a validated prediction interval for your child.
Read the primary trial for this result · Research on interpreting and extrapolating myopia-control efficacy
Explore the follow-up research. These results describe specific study periods and groups, separately from the prescription scenarios above.
After six or three years of MiSight, participants changed to single-vision contacts for one year. These are the additional changes during year 7, when participants were approximately 14–19 years old.
| Study regimen | Prescription change | Eye growth |
|---|---|---|
| After 6 years of MiSight | −0.21 D | +0.10 mm |
| After 3 years of MiSight | −0.23 D | +0.09 mm |
The study compared these results with age-based modeled expectations. It found no statistically significant excess over expected progression. The older participants and one-year follow-up limit how far the findings apply to younger children or later years.
Inputs stay in this page’s memory and clear when it reloads. Educational scenarios support a conversation with your child’s eye-care clinician.
| Treatment | Study period | Prescription result | Eye-growth result |
|---|---|---|---|
| Stellest | 2 years; FDA-reviewed study | 71% less progression | 53% less elongation |
| MiSight 1 day | 3 years; randomized trial | 59% less progression | 52% less elongation |
| Atropine 0.05% | 1 year; LAMP trial | −0.27 D vs −0.81 D | 0.20 mm vs 0.41 mm |
These trials used different study populations and comparison groups. Ages, populations, follow-up periods, adherence, and control treatments differed. Comparing treatment choices requires attention to each study’s population, methods, and your child’s clinical needs. Stellest is our preferred spectacle-lens approach. We choose treatment according to each child’s needs and the evidence relevant to them.
We review the starting prescription, family history, eye health, and axial length, then select a treatment the family can follow consistently. We generally measure eye length two to three times a year, with timing tailored to the child. Wear time, comfort, prescription change, and eye growth guide follow-up decisions.
Outdoor time and breaks from prolonged near work are useful habits to discuss alongside treatment. A school-based randomized trial in China found that additional outdoor time reduced new-onset myopia; that is different from proving treatment of established myopia. They support the prescribed myopia-control plan. Treatment often continues through the years when the eye is still growing.
PRACTICAL ANSWERS
Current treatments aim to slow further progression. Your child continues to use an appropriate prescription for clear vision.
Yes. Stellest spectacle lenses are our primary option to discuss for children who meet the treatment criteria. Your doctor checks age, prescription, and eye health.
We compare prescription changes and axial-length measurements over time, alongside wear habits and eye health. No single visit or percentage predicts an individual child’s outcome.
We primarily discuss Stellest spectacle lenses, then MiSight daily disposable contact lenses, and 0.05% atropine when appropriate. Selection depends on age, prescription, eye health, progression, and the family’s ability to follow the treatment plan.
Yes. Midtown uses a ZEISS IOLMaster optical biometer to measure axial length, the front-to-back length of the eye. We assess changes alongside prescription measurements and generally monitor eye length two to three times a year, with timing individualized.
Stellest uses lenslets in spectacle lenses; MiSight uses treatment zones in a daily contact lens; Midtown’s atropine option uses prescribed 0.05% eye drops. All aim to slow further progression. Each option has been studied in separate trials with different participants and methods. Atropine for myopia is off-label.
Our explorer combines observed treatment averages with clearly labeled untreated scenarios through five years for Stellest/HAL and 0.05% atropine, and six years for MiSight. After each trial’s untreated comparison ends, dashed lines use published assumptions about slowing progression with age. These group-average illustrations have greater uncertainty than observed randomized comparisons. Your child’s examination and repeat measurements guide care.
Reference measurements vary with age, sex, population, and refractive error. One European cohort analysis reported mean eye lengths of 22.36 mm at age 6, 23.10 mm at age 9, and 23.41 mm at age 15. These population averages provide context. We interpret repeat IOLMaster measurements alongside your child’s prescription and examination.
The figures are population odds ratios associated with broad prescription categories. They describe associations with myopic macular degeneration, retinal detachment, posterior subcapsular cataract, and open-angle glaucoma. A personal lifetime percentage or a treatment-specific reduction in these diseases requires evidence beyond the childhood treatment trials.
Midtown uses 0.05% atropine. The LAMP trials studied this concentration, including continued treatment through five years. Atropine use for myopia is off-label in the United States; your doctor discusses benefits, side effects, follow-up, and stopping decisions.
Explore the longer-term studies →The 2026 LAMP report studied two discontinuation strategies after five years of follow-up. During year six, one group tapered from 0.05% to 0.025%, while the other remained on 0.05%; both stopped for years seven and eight. The taper group had less average progression across those three years. The authors describe the clinical importance of the prescription difference as uncertain. Your doctor guides changes to treatment.
Explore the longer-term studies →These educational resources support a conversation with your eye doctor. Your examination and medical history guide individual treatment decisions.
MIDTOWN OPTOMETRY · SANTA CRUZ